INTRODUCTION
Health professionals, including physicians, nurses, and pharmacists, play a central role in providing essential health care for the population. They are frequently exposed to multiple factors affecting their psychological and mental health, which, in turn, affects the quality of care toward their patients (Junne et al., 2018). Thus, the mental health and well-being of health-care providers and its influence on patient safety is gaining more attention worldwide.
Persistent stress can lead to the burnout syndrome. Burnout is defined as a prolonged response to chronic emotional and interpersonal stressors at work (Maslach & Leiter, 2016; Soto-Rubio et al., 2020). Consequently, burnout may lead to absenteeism, psychological problems, and eventually depression and drug consumption (ibid.). The three major domains of burnout syndrome include: (1) emotional exhaustion (EE), (2) depersonalization (DP) and cynicism, and (3) professional inefficacy. Exhaustion refers to the feeling of being used up and lacking energy to face another day at work. Cynicism is the negative response toward the job, including a loss of idealism, and professional inefficacy is the lack of productivity (Maslach & Leiter, 2016).
A meta-analysis conducted among nurses showed that the prevalence of burnout is 51.98% (Zhang et al., 2018). Another systematic review showed that overall burnout among physicians is estimated at 67% (Rotenstein et al., 2018). For pharmacists, burnout depends on their practice setting, leading to higher burnout rates among community pharmacists (Mott et al., 2004). Several studies suggest that emotional intelligence can affect burnout (van Dusseldorp et al., 2011).
The term emotional intelligence was first described by Salovey and Mayer in 1990 as a type of intelligence in which one can control and understand his own and others’ emotions as well their ability to guide their thinking and actions. It was known as the ability model. Emotional intelligence was divided into four skills: (1) perceiving emotions, (2) using emotions to facilitate thoughts, (3) understanding emotions, and (4) managing emotions in order to promote personal and social growth (Mott et al., 2004). In this context, many studies highlight the importance of emotional intelligence to develop personal well-being and the positive association between emotional intelligence and many skills such as leadership, job satisfaction, high performance, and team effectiveness, which can be classified under the soft skills category (Dacre Pool & Qualter, 2012; Brackett et al., 2012; Druskat et al., 2013)
Soft skills, defined as interpersonal characteristics, are widely known as people skills and personal qualities (Robles et al., 2012). The seven main soft skills include: communication skills, team work skills, critical thinking and problem solving, entrepreneurship, ethics and professional moral skills, leadership skills, and lifelong learning skills (Ngoo et al., 2015). Thus, many medical schools are focusing on one's personality and behaviors, so that they acquire the essential knowledge to develop their competencies (Choi et al., 2014).
In Lebanon, many studies focusing on burnout were conducted among pharmacists, medical students, and nurses, which showed higher burnout rates in comparison with other countries (Lahoud et al., 2019; Talih et al., 2018, 2016). However, to the best of our knowledge, there is no clear data regarding the effect of emotional intelligence and soft skills on burnout. Moreover, Lebanon is facing now, more than ever, an exceptional economical and sanitary situation. This, in addition to the fact that Lebanese people rarely seek for psychological support, might affect health providers’ well-being (Karam et al., 2018).
The main objective of our study is to assess the effect of soft skills and emotional intelligence on burnout among health-care professionals in Lebanon. As for the tested hypothesis, the null hypothesis (H0) is: there is no association between soft skills and emotional intelligence of health professionals with burnout, while the alternative hypothesis (H1) is: there is an association between soft skills and emotional intelligence of health professionals with burnout.
MATERIALS AND METHODS
Study design
A cross-sectional study was conducted among working health-care professionals all over Lebanon for a period of 3 months starting from March, when our first participant was recruited, till June 2021, when our data collection ended.
The questionnaire included three main parts and required 7–10 min to complete. It was first written in English and then translated to Arabic in order to target a larger number of participants.
The first part included sociodemographic questions such as those on age, gender, residence, profession, and working region. The second part aimed at work conditions such as working schedule, work type, years of working experience, and job satisfaction. The third part of the questionnaire included the Maslach Burnout Inventory for Health Services Survey (MBI-HSS) and the Trait Meta-Mood Scale (TMMS-24) to assess emotional intelligence, as well as a soft skill assessment scale using a five-point Likert scale ranging from strongly disagree (=1) to strongly agree (=5).
Tools
All the scales used were already developed and validated. The TMMS-24 was used to assess emotional intelligence. It is a version of the Trait-Meta Mood Scale (TMMS), which was originally developed by Salovey et al. (1995) and reduced and validated by Fernández-Berrocal et al. (2004); the scale had a Cronbach α = 0.929. Burnout was assessed using the MBI-HSS, which comprises 22 items regrouped into three subscales: EE, DP, and personal accomplishment (PA) (Ibtissam et al., 2012); it had a Cronbach α = 0.842. The soft skills scale was adapted from Nikitina and Furuoka (2012); it had a Cronbach α = 0.972.
Data collection
The study was carried out via an online survey targeting health-care professionals from all the Lebanese districts. The data collection lasted approximately 4 months during which a questionnaire, developed through a Google form, based on our literature search, was sent and completed online via social networks using the snowball technique.
Study population
The main inclusion criteria were: (1) being a health-care professional; (2) currently working; (3) having a minimum working experience of 2 years; and (4) providing their written consent to participate in the study. Of the 345 contacted participants, 21 were excluded, which led to a total of 324 participants randomly recruited from all over Lebanon, including physicians, nurses, pharmacists, and other health-care professionals. Among the excluded participants, five were not health-care professionals and nine had not been working for 2 years or more, of which one was not currently employed and others were duplicates.
Sample size
We calculated the minimum required sample size using Epi Info version 7.2.4.0. Based on a systematic review conducted by Parola et al. (2017), we found that the prevalence of burnout among health-care professionals is estimated at 17.3%. With an acceptable margin of error of 5%, a design effect and a cluster of 1, and a 95% confidence interval (CI), our estimated minimum required sample size was 220 health-care professionals.
Ethical considerations
Taking the fact that this is an observational study, the Lebanese University ethics committee waived the need for approval, provided that consent is obtained from participants and their confidentiality and anonymity are maintained.
Statistical analysis
SPSS 25 for Windows was used for analyzing the data. Regarding the bivariate analysis, T test, Mann–Whitney test, analysis of variance (ANOVA), and Kruskal–Wallis tests were used to compare the means, whenever the association between a qualitative and a quantitative variable was tested.
Pearson and Spearman correlations were used to test the association between two quantitative variables. P-value <0.05 was considered as significant, and the CI was set at 95%. A Cronbach alpha was recorded for reliability analysis of all the scales.
A linear regression was used to assess the effect of soft skills and emotional intelligence on burnout. Variables with a P-value <0.2 were included in the multivariable analyses.
RESULTS
Profile of the participants
A total of 345 health-care workers participated in this study; of them, 324 were included, involving 45.1% nurses, 32.1% pharmacists, and 8.3% physicians. The mean age of the participants was 30.95 ± 8.69 years, and the majority of them were females (80.2%). As for their region of residence and work, the majority of them were from Mount Lebanon (see Table 1).
Table 1
Sociodemographic characteristics of the sample population.
| Variable | Frequency (%) |
|---|---|
| Gender | |
| Male | 64 (19.8%) |
| Female | 260 (80.2%) |
| Profession | |
| Nurse | 146 (45.1%) |
| Pharmacist | 101 (32.1%) |
| Physician | 27 (8.3%) |
| Other1 | 50 (15.4%) |
| Region of residence | |
| Beirut | 58 (17.4%) |
| Mount Lebanon | 214 (66.0%) |
| North | 21 (6.5%) |
| South | 13 (4.0%) |
| Nabatieh | 7 (2.2%) |
| Bekaa | 9 (2.8%) |
| Akkar | 1 (0.3%) |
| Baalbek/Hermel | 1 (0.3%) |
| Region of work practice | |
| Beirut | 128 (39.5%) |
| Mount Lebanon | 155 (47.8%) |
| North | 12 (3.7%) |
| South | 14 (4.3%) |
| Nabatieh | 6 (1.9%) |
| Bekaa | 7 (2.2%) |
| Akkar | 1 (0.3%) |
| Baalbek/Hermel | 1 (0.3%) |
| Mean ± SD | |
| Age | 30.95 ± 8.69 |
| Working experience in years | 8.08 ± 7.96 |
| Working hours per week | 41.59 ± 14.29 |
Soft skills
The soft skills scale was not normally distributed, with a mean ± SD of 138.59 ± 18.33.
Soft skills were significantly associated with profession (P = 0.008), age, working experience in years, emotional intelligence, and burnout (P < 0.001). A positive, yet weak correlation was found between soft skills and emotional intelligence (R = 0.382). As for burnout, a negative, yet weak correlation was found with soft skills (R = −0.278; see Table 2).
Table 2
Soft skills, emotional intelligence, and burnout: bivariate analysis/
| Soft skills | Emotional intelligence | Burnout | ||||
|---|---|---|---|---|---|---|
| Variable | Mean ± SD/R | P-value | Mean ± SD/R | P-value | Mean ± SD/R | P-value |
| Gender | ||||||
| Male | 141.14 ± 18.36 | 0.158 | 86.15 ± 17.45 | 0.653 | 56.515 ± 12.110 | 0.052 |
| Female | 137.97 ± 18.30 | 87.21 ± 14.35 | 59.669 ± 11.430 | |||
| Profession | ||||||
| Nurse | 138.10 ± 18.13 | 0.008 | 87.17 ± 15.56 | 0.500 | 60.452 ± 11.082 | 0.010 |
| Pharmacist | 136.52 ± 18.44 | 86.63 ± 15.07 | 59.584 ± 11.704 | |||
| Physician | 135.22 ± 18.57 | 83.66 ± 15.92 | 58.481 ± 13.351 | |||
| Other1 | 146.04 ± 17.11 | 89.08 ± 12.49 | 54.160 ± 10.997 | |||
| Region work | ||||||
| Beirut | 138.72 ± 19.12 | 0.623 | 86.89 ± 15.85 | 0.940 | 61.078 ± 11.482 | 0.034 |
| Mount Lebanon | 138.65 ± 18.59 | 86.89 ± 15.22 | 57.503 ± 11.174 | |||
| Other2 | 137.97 ± 14.87 | 87.78 ± 11.12 | 58.536 ± 12.950 | |||
| Region residence | ||||||
| Beirut | 138.37 ± 16.56 | 0.402 | 87.00 ± 13.62 | 0.781 | 61.603 ± 11.581 | 0.094 |
| Mount Lebanon | 138.93 ± 19.76 | 86.69 ± 16.00 | 58.088 ± 11.366 | |||
| Other2 | 137.46 ± 13.75 | 88.32 ± 12.01 | 60.134 ± 12.360 | |||
| Job satisfaction | ||||||
| Yes | 138.50 ± 19.61 | 0.594 | 86.54 ± 16.34 | 0.394 | 56.317 ± 11.133 | <0.001 |
| No | 138.79 ± 15.6 | 87.90 ± 11.96 | 64.354 ± 10.706 | |||
| Age | R = 0.238 | 0.000 | R = 0.060 | 0.281 | R = −0.19 | 0.727 |
| Working experience (years) | R = 0.222 | 0.000 | R = 0.030 | 0.596 | R = 0.040 | 0.468 |
| Working hours (week) | R = 0.021 | 0.700 | R = 0.046 | 0.405 | R = −0.007 | 0.893 |
| Emotional intelligence | R = 0.382 | 0.000 | - | - | R = −0.169 | 0.002 |
| Burnout | R = −0.278 | 0.000 | R = −0.169 | 0.002 | - | - |
| Soft skills | - | - | R = 0.382 | 0.000 | R = −0.278 | 0.000 |
Emotional intelligence
Emotional intelligence was normally distributed with a mean ± SD of 87.00 ± 14.99. Emotional intelligence was significantly associated with soft skills (R = 0.382) and burnout (R = −0.169; see Table 2).
Burnout
The burnout scale was normally distributed with a mean ± SD of 59.04 ± 11.61.
Burnout was significantly associated with profession (P = 0.010), region of work (P = 0.034), job satisfaction (P < 0.001), soft skills (R = −0.278), and emotional intelligence (R = −0.169; see Table 2).
Predicting model for burnout
Based on the bivariate analysis, variables with a P-value <0.200 were included in the multivariate analysis in order to predict burnout. These variables were soft skills, emotional intelligence, job satisfaction, profession, work region, region of residence, and gender (see Table 3).
Table 3
Burnout's predicting model.
| Variable | Standardized β | B | CI | P-value | |
|---|---|---|---|---|---|
| Lower | Upper | ||||
| Soft skills | −0.216 | −0.137 | −0.207 | −0.067 | <0.001 |
| Emotional intelligence | −0.087 | −0.068 | −0.152 | 0.017 | 0.116 |
| Job satisfaction | −0.329 | −8.064 | −10.493 | −5.635 | <0.001 |
| Pharmacist | −0.063 | −1.576 | −4.462 | 1.310 | 0.283 |
| Physician | −0.027 | −1.122 | −5.706 | 3.466 | 0.631 |
| Other professions | −0.143 | −4.595 | −8.040 | −1.151 | 0.009 |
| Work Mount Lebanon | −0.107 | −2.496 | 0.666 | 1.502 | 0.075 |
| Work other | −0.258 | −9.015 | −16.379 | −1.651 | 0.017 |
| Residence Mount Lebanon | −0.072 | −1.776 | −5.252 | 1.701 | 0.316 |
| Residence other | 3.539 | 5.927 | −1.037 | 12.890 | 0.095 |
| Gender | −0.049 | 1.434 | 0.773 | 1.293 | 0.379 |
Higher burnout was associated with lower soft skills (β = −0.137) and lower job satisfaction (β = 8.064). Dentists, radiologists, midwives, nutritionists, psychotherapists, and speech therapists (grouped together in the variable “other professions”) had lower burnout levels than nurses (β = −4.595). As for burnout among pharmacists and physicians, no significant difference was found compared to nurses (P = 0.283 and 0.631, respectively). Moreover, it is worth noting that people working i n Baalbek, Akkar, Beqaa, North and South had lower burnout levels compared to those working in Beirut (β = −9.015). As for emotional intelligence, no statistically significant association was found with burnout (P = 0.116), as well as with gender and region of residence (see Table 3).
DISCUSSION
Key results
This study aimed at testing the effect of soft skills and emotional intelligence on burnout among health-care professionals in Lebanon. The main findings showed that better soft skills lead to lower burnout. It is worth noting that the bivariate analysis showed a significant association between burnout and emotional intelligence. These results are in line with previous findings which showed that health-care professionals with higher emotional intelligence experienced less EE and DP (Ünal et al., 2014). Another study conducted in Tehran showed that emotional intelligence was negatively associated with EE (Mansoor et al., 2011).
The health and political situation that Lebanon is facing might demotivate health professionals, leading to high levels of job burnout (Harari et al., 2017). In fact, based on previous literature, physicians and nurses are more likely to experience burnout. A meta-analysis conducted by Gómez-Urquizaetal et al. (2017) showed that 30% of emergency nurses experienced at least one of the three Maslach Burnout Inventory subscales. This can be explained by the fact that nurses are in direct contact with the patient, which automatically puts them under pressure, in addition to their work schedule and work load.
As for physicians and medical students, a study conducted in the USA showed that 50%–60% had at least one of the burnout symptoms (Rothenberger et al., 2017).
In the Arab countries such as Saudi Arabia, Jordan, and Lebanon, a systematic review showed that high levels of burnout were reported among nurses (Al-Turki et al., 2010. Elbarazi et al., 2017; Ibtissam et al., 2012).
Furthermore, a systematic review showed that 20%–81% of health-care workers experience high levels of EE, 9.2%–80% experience high DP levels, while 13.3%–85.8% have low PA levels (Lahoud et al., 2019). In Lebanon, similar results were found in a study conducted among nurses where job satisfaction was significantly associated with burnout and nurses experienced moderate burnout levels (Ibtissam et al., 2012).
In addition, a positive association was found between soft skills and emotional intelligence. This replicates other published data regarding the effect of soft skills such as leadership, communication, and job satisfaction on emotional intelligence (Brackett et al., 2011; Dacre et al., 2012). Health-care workers with higher soft skills have better self-confidence and improved interpersonal, leadership, and communication skills, which improves their capacity to manage their social and personal emotions, which, in turn, eventually improves their emotional intelligence (Harari et al., 2017). According to previous literature, nurses improve their mental health, communication capability, and job productivity after undergoing a communication skills training. Also, 60% of oncology physicians who attended communication skills workshops had the sense of PA (Rothenberger et al., 2017; Elbarazi et al., 2017; Al-Turki et al., 2010).
Finally, this study also showed that health-care professionals who were satisfied with their job had a significantly lower job burnout. Also, people working in Beirut had a higher burnout level comparing to those who work in Baalbek, Akkar, Beqaa, North and South. This may be related to the stress experienced by the health-care professionals due to the overpopulation in Beirut. Further studies are suggested to explain these contextual findings.
Clinical implications
Since this study confirmed the impact of soft skills and emotional intelligence on burnout among health-care professionals in Lebanon, many interventions can be suggested in order to reduce burnout levels.
This will consequently reduce work fatigue and improve their mental health and physical well-being. Thus, training health-care professionals during their education will improve their soft skills and emotional intelligence, and consequently improve their behavior in stressful situations and reduce their job burnout. Subsequently, during their work journey, many interventions can be addressed, including reducing their working hours, increasing their financial income, and providing them with the needed psychological support (Rahme et al., 2020).
Study limitations and strengths
The limitations of this study are as follows:
First, regarding participants, the sample mainly included nurses and pharmacists with no physicians and other health-care professionals. Moreover, the majority of the participants were from Beirut and Mount Lebanon. This might be related to the background of the researchers, in addition to the fact that physicians were not cooperative. In addition, due to the economic situation in Lebanon, many health workers were unemployed, which affected our sample size. As for the gender distribution, the majority were females, which reflects the demographic characteristics of health workers in Lebanon. Second, since we used the snowball technique, we could not know the number of health workers that received the questionnaire, and thus, we could not calculate the response rate. These factors collectively affected the representativeness of our sample.
In addition, many factors were not addressed during data collection, such as financial situation and income, psychological support, and antipsychotics consumption (Fond et al., 2019).
A volunteer bias might thus be present since it is an observational study and participants had the option to refuse participation. In addition, a non-response bias might as well occur, which affects the precision of the study by reducing the sample size.
Third, the scales used in this study are not validated in Lebanon, which might cause some non-differential information bias. Furthermore, the collected data was based on self-reported measures, which may lead to an information bias.
Despite the previously mentioned limitations, our study had many strengths. In fact, the questionnaire was developed in two languages, targeting a larger number of participants. Moreover, it mainly included short questions and the scales were frequently used in the reviewed literature and were validated outside Lebanon. Regarding the minimum required sample size, it was around 220 participants, while our study included 324 health-care professionals, which increased the precision of the outcomes and might have ensured a good representativeness of the Lebanese health-care professionals, especially nurses and pharmacists, thus improving the generalizability of our results. Finally, additional research should be conducted using other methods in order to support our findings. The authors assumed that the obtained results are original and similar to other recent studies.
CONCLUSION
In conclusion, this study showed that soft skills and emotional intelligence can affect job burnout. Moreover, soft skills were significantly associated with emotional intelligence.
Further studies should highlight the effect of soft skills and emotional intelligence of health professionals on burnout in order to improve the mental status of the Lebanese health workers and the quality of care toward their patients.
In addition, continuing education related to improving emotional intelligence and soft skills should be offered to health-care professionals, highlighting their importance and their impact on burnout during the current crisis. Finally, other hypotheses should be tested regarding the effect of burnout, emotional intelligence, and soft skills on patient care and safety.
Acknowledgment
The authors would like to thank Professor Pascale Salameh for her help throughout the study.
Notes
[4] Conflicts of interest Conflict of interest
None.
APPENDIX
1
Questionnaire
Soft skills and emotional intelligence: effect on burnout and competence/
Dear health-care professional,
This questionnaire aims to collect information about the effect of soft skills and emotional intelligence on burnout and competence among health workers. Kindly note that the collected information is completely anonymous and confidential. It will only take about 7 min of your time. Furthermore, you have the ability to quit at any time. Thank you for taking part in this.

Inclusion Criteria: If all the answers to this section are “Yes,” Kindly proceed to the next section/

1 Are you a health-care professional?/
Yes –
 No –

2 Do you have a working permit offered by the Ministry of Public Health?/

Yes –
 No –

3 Are you registered to your syndicate?/
Yes –
 No –

4 Are you currently employed?/

Yes –
 No –

5 Have you been working for 2 years or more?/
Yes –
 No –

6 Would you like to participate in our study?/
Yes –
 No –

Sociodemographic information/

7 Gender/

Male –

Female –

8 Age/
 - Kindly write your age in years/

9 Region of residence/

Beirut –
 Mount Lebanon -
 North –
 Bekaa –
 South –
 Nabatieh –
 Baalbek/Hermel -
 /
 Akkar –

10 Profession/

Physician –
 Nurse -
 Pharmacist –
 Dentist -

11 Region of work practice/

Beirut –
 Mount Lebanon -
 North –
 Bekaa –
 South –
 Nabatieh –
 Baalbek/Hermel -
 Akkar –

Professional information/

12 Current position at work/
13 Working hours per week/
14 Work experience in years/
15 Are you satisfied with your current job?/
Yes – No
16 Are you confident about your work competence?/
Yes – No
Soft skills/emotional intelligence and burnout -
Strongly disagree/
 - Disagree/
 - Neutral/
 - Agree/
 - Strongly agree/

Soft skills: Are you able to/

Deliver idea clearly with confidence, both in written and oral forms/
Practice good listening skills and give response/
Give presentation clearly with confidence, according to the level of the audience/
Use technology during presentation/
Negotiate and reach a consensus/
Communicate with people from different cultural background/
Expand one's own communicative skill/

Use non-oral skills/
Identify and analyze problems in a complex situation and make justifiable evaluation/

Expand and improve one's thinking skills such as to explain, analyze, and evaluate a discussion/

Find ideas and alternative solutions/
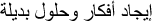
Think out of the box/
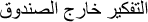
Make conclusions based on valid proof/
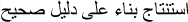
Keep going and give full attention to the given task/
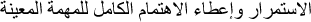
Understand and adapt oneself to the culture of the community and new working environment/


Identify business opportunities/
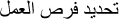
Estimate business plan/
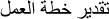
Create, explore, and seek business and job opportunities/
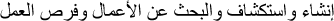
Be self-employed/

Understand the effects of economic, environmental, and sociocultural factors on the professional practice/
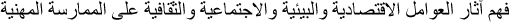
Analyze and make decisions in solving ethics-related issues/
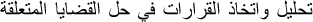

Practice ethical behavior and have a sense of responsibility toward society/
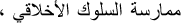
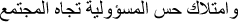
Lead a project/

Understand and act interchangeably as a group leader and a group member/
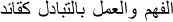

Contribute to teambuilding and work/
Supervise team members/
Search and manage relevant information from various sources/

Receive new ideas and capable of self-learning/
Develop an inquiring mind, and thirst for knowledge and learning/
Build good relations and have good interaction with other people and work with them effectively to achieve common goal/
Understand and switch between the roles of the group leader and a team member/
Recognize and respect the attitudes, behaviors, and beliefs of other people/
Contribute to the planning and coordinate the group work/
Emotional intelligence scale/

I pay a lot of attention to my feelings/

I am usually very conscious of what I feel/
I usually spend time thinking about my emotions/
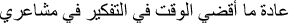
I think my emotions and state of mind deserve to be paid attention to/
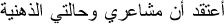

I allow my feelings to affect my thoughts/
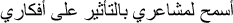
I constantly think about my state of mind/
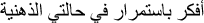
I often think about my feelings/
I pay a lot of attention to the way I feel/
My feelings are clear to me/
I can usually define my feelings/
I nearly always know how I feel/

I usually know how I feel about people/
I often become aware of my feelings in different situations/
I can always say how I feel/
I can sometimes say which emotions I am experiencing/

I can manage to understand my feelings/
I usually have an optimistic outlook, although I sometimes feel sad/

Even when I feel sad, I try to think about pleasant things/

When I am sad, I think about all life’s pleasures/

I try to have positive thoughts even when I feel bad/
If I think about things too much and end up complicating them, I try to calm myself down/

I am concerned about having a good state of mind/
I have a lot of energy when I feel happy/
When I am angry, I try to change my state of mind/
Burnout scale/

I feel emotionally drained from my work/
I feel used up at the end of the workday/
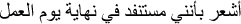
I feel fatigued when I get up in the morning and have to face another day on the job/

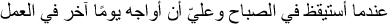
I can easily understand how my patients–colleagues feel about things/
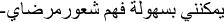
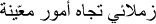
I feel I treat some patients–colleagues as if they were impersonal objects/
Working with people all day is really a strain for me/

I deal very effectively with the problems of my patients–colleagues/
I feel burned out from my work/

I feel I’m positively influencing other people’s lives through my work/
I’ve become more hard toward people since I took this job/

I worry that this job is hardening me emotionally/
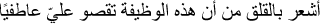
I feel very energetic/
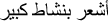
I feel frustrated by my job/
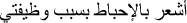
I feel I’m working too hard on my job/
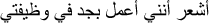
I don’t really care what happens to some patients–colleagues/

Working with people directly puts too much stress on me/

I can easily create a relaxed atmosphere with my patients–colleagues/
I feel happy after working closely with my patients–colleagues/
I have accomplished many worthwhile things in this job/

I feel like I’m at the end of my rope/
In my work, I deal with emotional problems very calmly/
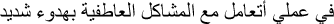
I feel patients–colleagues blame me for some of their problems/