
Table 1.
Interview schedule.
| No. | Interview questions |
|---|---|
| 1 | How do monitoring alarms affect your practice? What is the role of monitor alarms in your practice? |
| 2 | What is your perception of the number of monitor alarms on your unit? |
| 3 | What do you see as the benefits and challenges of the alarms on your unit? |
| 4 | Who responds to alarms on your unit? What factors do you think affect your response to alarms? When do you communicate with other nurses about your alarm settings? What policies and procedures, official or unofficial, exist on your unit related to alarms? How did you learn to use the monitors? How does the acuity of the patient influence your alarm management? |
| 5 | What do you see as the purpose of customizing alarms? How often do you need to customize alarms from the default settings? What types of alarms do you think you customize most often? One way people sometimes customize alarms is by changing the alarm limits. If you decide an alarm limit needs to be customized, how do you determine how much to change the limit? |
| 6 | What does the term alarm fatigue mean to you? |
Table 2.
Sociodemographic data.
| Variable | N (%) | M (SD) |
|---|---|---|
| Gender | ||
| Male | 20 (33.3) | |
| Female | 40 (66.7) | |
| Age (years) | 26.2 (7.16) | |
| 18–25 | 31 (51.7) | |
| 25–30 | 18 (30.0) | |
| 30–35 | 7 (11.7) | |
| 35–45 | 2 (3.30) | |
| >45 | 2 (3.30) | |
| Years of experience | 6.4 (7.70) | |
| 0.5–1 | 6 (10.0) | |
| 1–3 | 25 (41.7) | |
| 3–6 | 9 (15.0) | |
| 6–10 | 13 (21.7) | |
| >10 | 7 (11.7) | |
| Department | ||
| ICU | 26 (43.3) | |
| Neuro ICU | 5 (8.30) | |
| CCU | 6 (10.0) | |
| NICU | 21 (35.0) | |
| PICU | 2 (3.30) |
Table 3.
Clinical alarm survey results compared with published studies.
| Questions | Clinical alarms survey (n = 60) |
|---|---|
| Nuisance alarms | |
| Nuisance alarms occur frequently | 68.3 |
| Nuisance alarms disrupt patient care | 72 |
| Nuisance alarms reduce trust in alarms and cause caregivers to turn alarms off at times other than setup or procedural events | 61.7 |
| Experience with alarms | |
| Properly setting alarm parameters and alerts is overly complex in existing devices | 38.3 |
| New (<3 years old) monitoring systems have solved most of the previous problems we experienced with clinical alarms | 58.3 |
| The alarms used on my floor/area of the hospital are adequate to alert staff of potential or actual changes in a patient’s condition | 81.7 |
| There have been frequent instances where alarms could not be heard and were missed | 40 |
| The staff is sensitive to alarms and responds quickly | 71.7 |
| When several devices with alarms are used with a patient, it can be confusing to determine which device is in the alarm | 45 |
| Environmental background noise has interfered with alarm recognition | 48.3 |
| Alarm sounds and/or visual displays should differentiate the priority of the alarm | 90 |
| Alarm sounds and/or visual displays should be distinct based on the parameter or source (e.g. device) | 83.3 |
| Alarms should impact multiple senses (audible, visual, proprioceptive, etc.) | 90 |
| Alarm notification | |
| The purpose of clinical alarms is to alert staff of an existing or potentially hazardous patient condition | 88.3 |
| The medical equipment used on my unit/floor all have distinct outputs (sounds, repetition rates, visual displays, etc.) that allow differentiation of the source of the alarm | 61.7 |
| A central alarm management staff that receives alarm messages and notifies the appropriate staff is helpful | 75 |
| Alarm integration and communication systems via pager, cell phone, and other wireless devices are useful in improving alarm management and response | 65 |
| Smart alarms | |
| Smart alarms, where multiple parameters, rate of change of parameters, and signal quality, are automatically assessed in their entirety would be effective in reducing false alarms | 63.3 |
| Smart alarms, where multiple parameters, rate of change of parameters, and signal quality, are automatically assessed in their entirety would be effective in improving clinical response to important patient alarms | 71.7 |
| Institutional requirement | |
| Policies and procedures exist within the facility to regulate alarms and they are followed | 60 |
| There is a requirement in your institution to document that the alarms are set and are appropriate for each patient | 70 |
Table 4.
Ranked issues of importance regarding alarms.
| No. | Variables | Mean | Ranking |
|---|---|---|---|
| 1 | Difficulty in setting alarms properly. | 3.92 | 7th |
| 2 | Difficulty in hearing alarms when they occur. | 3.58 | 3rd |
| 3 | Difficulty in identifying the source of an alarm. | 3.82 | 5th |
| 4 | Difficulty in understanding the priority of an alarm. | 4.00 | 8th |
| 5 | Frequent false alarms, lead to reduced attention or response to alarms when they occur. | 3.32 | 1st |
| 6 | Inadequate staff to respond to alarms as they occur. | 3.321 | 2nd |
| 7 | Over-reliance on alarms to call attention to patient problems. | 3.73 | 4th |
| 8 | Noise competition from non-clinical alarms and pages. | 4.08 | 9th |
| 9 | Lack of training on alarm systems. | 3.87 | 6th |
Table 5.
Difference of means in alarm’s perception and practice according to gender.
| Variables | M (SD) | t | P-value |
|---|---|---|---|
| Properly setting alarm parameters and alerts is overly complex in existing devices | 0.02* | ||
| Male | 3.80 (1.64) | 2.33 | |
| Female | 2.75 (1.65) | 2.33 | |
| Environmental background noise has interfered with alarm recognition | 0.01* | ||
| Male | 4.10 (1.37) | 2.47 | |
| Female | 2.95 (1.84) | 2.72 | |
| Difficulty in setting alarms properly | 0.05* | ||
| Male | 3.10 (1.92) | -1.8 | |
| Female | 4.33 (2.71) | -2.02 | |
| Difficulty in hearing alarms when they occur | 0.02* | ||
| Male | 2.85 (1.95) | -2.09 | |
| Female | 4.30 (2.78) | -2.34 |
Table 6.
Difference of means in alarm’s perception and practice according to age, years of experience, and hospital department.
| Variable | df | M | F | P-value |
|---|---|---|---|---|
| Age | ||||
| Nuisance alarms | 0.75 | 0.56 | ||
| BG | 4 | 2.01 | ||
| WG | 55 | 2.69 | ||
| Experience with alarms | 1.09 | 0.37 | ||
| BG | 4 | 32.87 | ||
| WG | 55 | 30.15 | ||
| Alarm notification | 0.42 | 0.79 | ||
| BG | 4 | 2.35 | ||
| WG | 55 | 5.6 | ||
| Smart alarms | 1.47 | 0.23 | ||
| BG | 4 | 2.33 | ||
| WG | 55 | 1.59 | ||
| Institutional requirements | 0.82 | 0.52 | ||
| BG | 4 | 2.41 | ||
| WG | 55 | 2.92 | ||
| Years of experience | ||||
| Nuisance alarms | 1.02 | 0.41 | ||
| BG | 4 | 2.68 | ||
| WG | 55 | 2.64 | ||
| Experience with alarms | 1.11 | 0.36 | ||
| BG | 4 | 33.34 | ||
| WG | 55 | 30.12 | ||
| Alarm notification | 0.29 | 0.88 | ||
| BG | 4 | 1.65 | ||
| WG | 55 | 5.65 | ||
| Smart alarms | 1.53 | 0.21 | ||
| BG | 4 | 2.42 | ||
| WG | 55 | 1.59 | ||
| Institutional requirements | 0.54 | 0.71 | ||
| BG | 4 | 1.6 | ||
| WG | 55 | 2.98 | ||
| Hospital Department | ||||
| Nuisance alarms | 0.96 | 0.44 | ||
| BG | 4 | 2.53 | ||
| WG | 55 | 2.65 | ||
| Experience with alarms | 1.02 | 0.4 | ||
| BG | 4 | 30.98 | ||
| WG | 55 | 30.29 | ||
| Alarm notification | 0.91 | 0.47 | ||
| BG | 4 | 4.93 | ||
| WG | 55 | 5.42 | ||
| Smart alarms | 0.47 | 0.76 | ||
| BG | 4 | 0.8 | ||
| WG | 55 | 1.7 | ||
| Institutional requirements | 1.29 | 0.29 | ||
| BG | 4 | 3.65 | ||
| WG | 55 | 2.83 |
Table 7.
Difference of means in alarm’s importance according to age, years of experience, and hospital department.
| Variable | df | M | F | P-value |
|---|---|---|---|---|
| Age | ||||
| Alarm importance ranking scale | 0.03* | |||
| BG | 4 | 547.27 | 2.86 | |
| WG | 55 | 191.3 | ||
| Difficulty in setting alarm properly | 0.05* | |||
| BG | 4 | 14.98 | 2.6 | |
| WG | 55 | 5.76 | ||
| Difficulty in understanding the priority of an alarm | 0.01* | |||
| BG | 4 | 20.88 | 3.61 | |
| WG | 55 | 5.79 | ||
| Years of experience | ||||
| Alarm Importance Ranking Scale | 0.12* | |||
| BG | 4 | 387.79 | 1.91 | |
| WG | 55 | 202.9 | ||
| Difficulty in setting alarm properly | 0.01* | |||
| BG | 4 | 20.03 | 3.72 | |
| WG | 55 | 5.39 | ||
| Difficulty in understanding the priority of an alarm | 0.00* | |||
| BG | 4 | 22.22 | 4.02 | |
| WG | 55 | 5.52 |
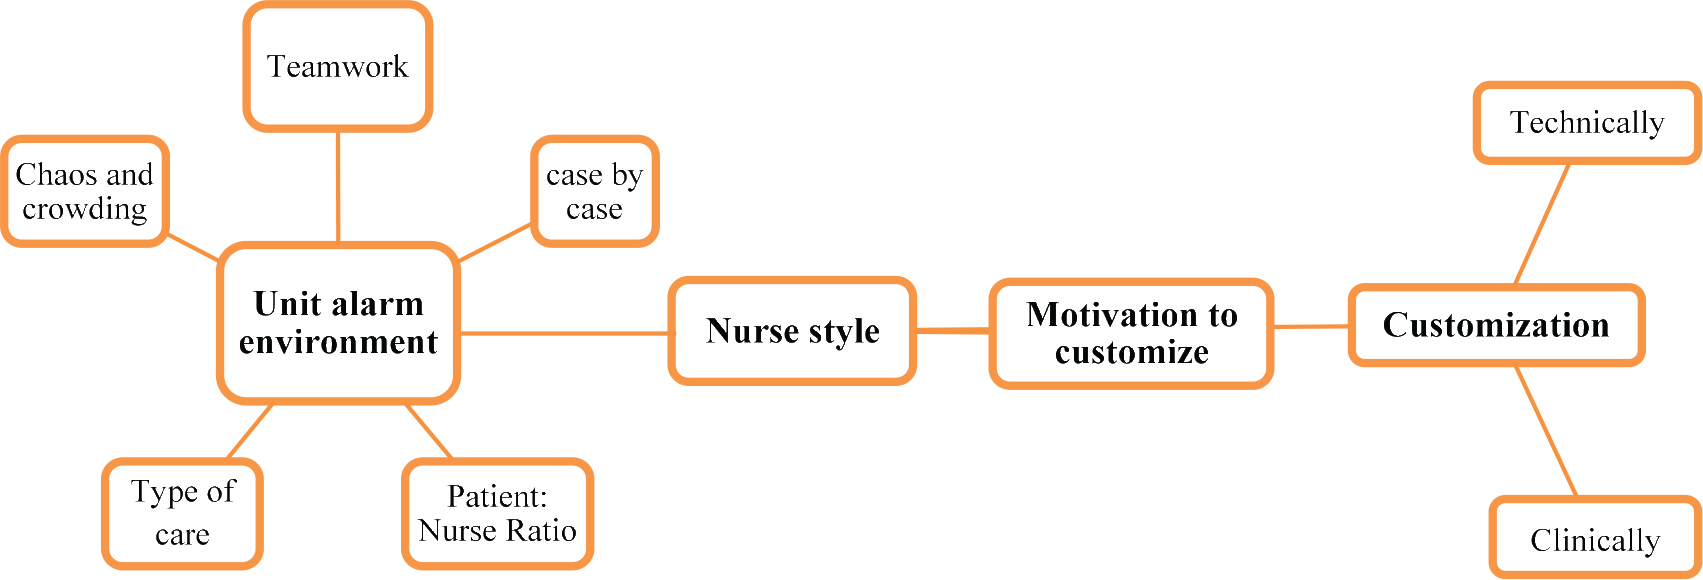
Figure 1.
Phenomenological themes concept map.