
Table 1.
Eligibility criteria
| PICOS | Inclusion criteria | Exclusion criteria |
|---|---|---|
| Population | Asymptomatic female |
|
| Intervention | DBT with/without DM | - Imaging is specifically used for diagnostic or surveillance purposes |
| Comparator | DM alone | - DM combined with any other supplemental screening modality |
| Outcomes |
| - NA |
| Study designs | Full economic evaluation, including CUA and CEA |
|
| Limit | Peer-reviewed articles |
|
[i] ADH, atypical ductal hyperplasia; ALH, atypical lobular hyperplasia; CBA, cost-benefit analysis; CEA, cost-effectiveness analysis; CUA, cost-utility analysis; DBT, digital breast tomosynthesis; DCIS, ductal carcinoma in situ; DM, digital mammography; Gy, gray (unit); ICER, incremental cost-effectiveness ratio; LCIS, lobular carcinoma in situ; LYs, life years; NA, not applicable; QALYs, quality-adjusted life years.
Table 2.
Databases searched
| Databases | Date parameters |
|---|---|
| MEDLINE via Ovid | 1946–June 18, 2025 |
| Embase via Ovid | 1974–June 18, 2025 |
| EB Health –KSR Evidence via Ovid | 2015–2025 week 24 |
| Cochrane Library via Wiley | Inception to present |
| NHS EED via https://www.crd.york.ac.uk/CRDWeb/ | Inception to March 2015 |
| CEA registry via https://cear.tuftsmedicalcenter.org | Inception to present |
| RePEc IDEAS via https://ideas.repec.org | Inception to present |
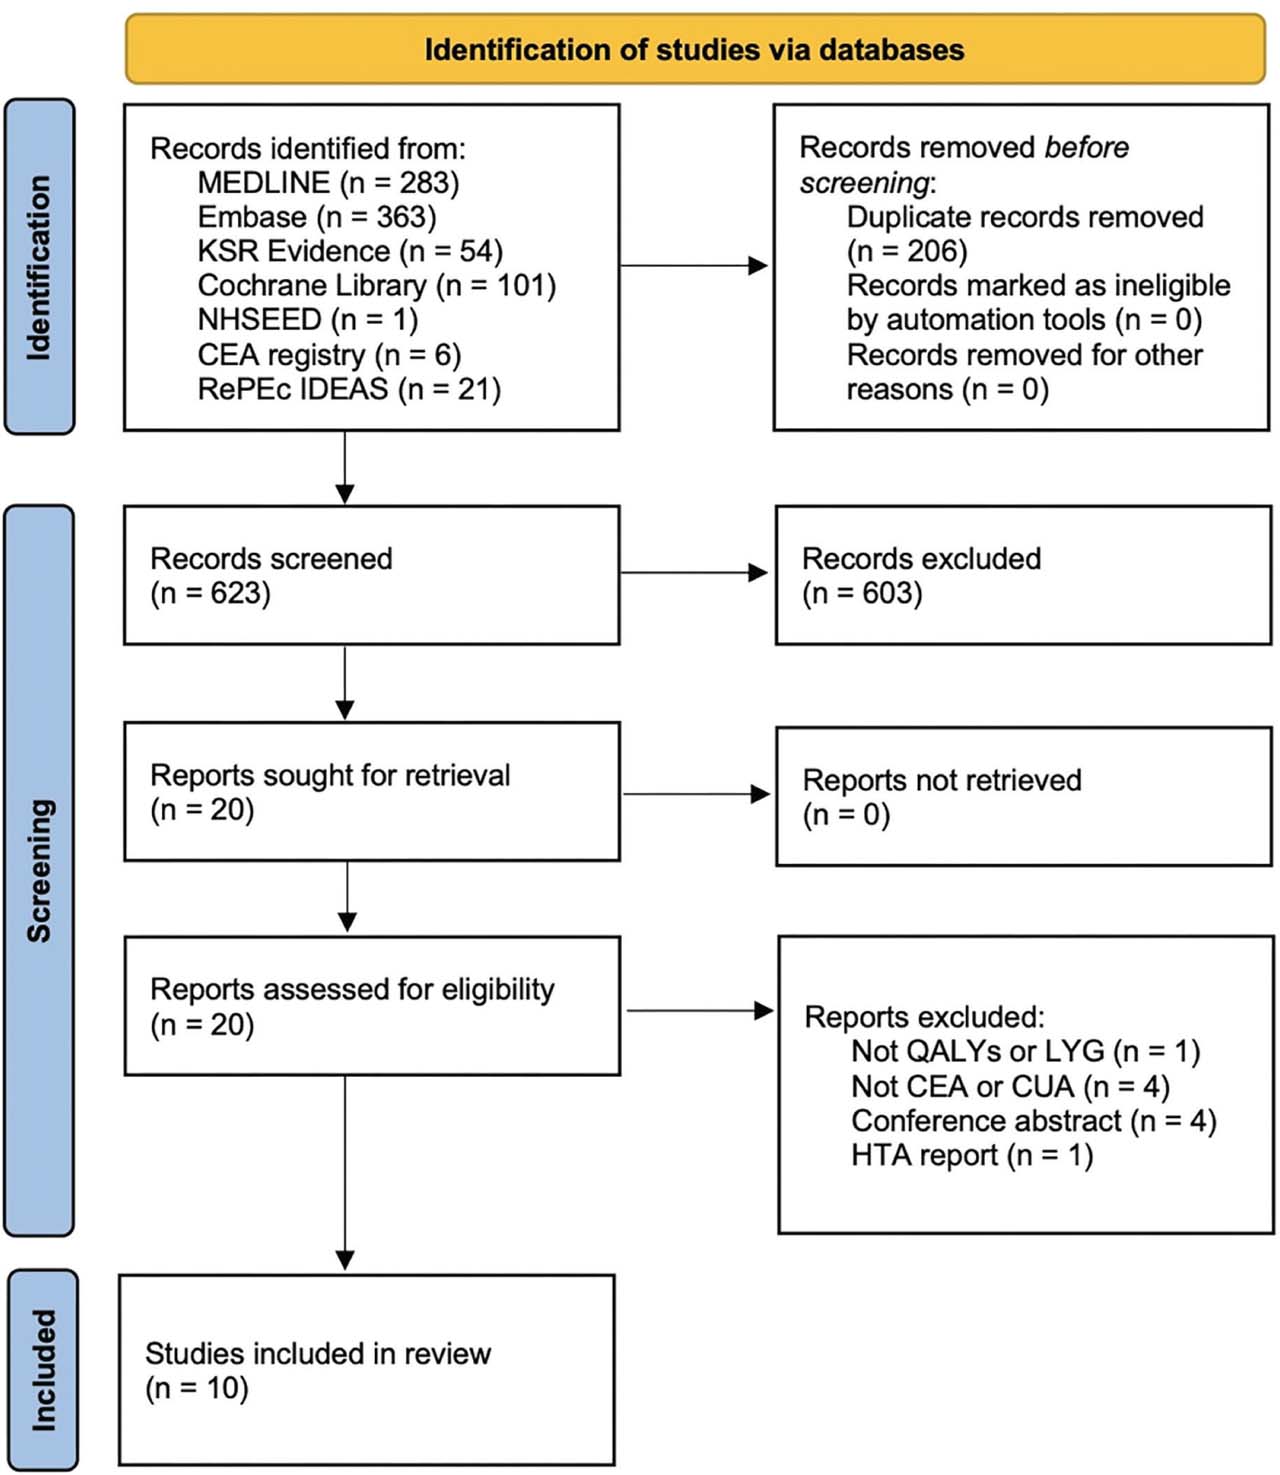
Figure 1.
PRISMA flow diagram for study selection.
CEA, cost-effectiveness analyses; CUA, cost-utility analyses; HTA, health technology assessment; LYG, life years gained; NHSEED, National Health Service Economic Evaluation Database.
Table 3.
Characteristics of included studies
| Publication | Country | Study population | Intervention | Screening interval | Primary economic evaluation outcome | Industry funding |
|---|---|---|---|---|---|---|
| Chung et al. 2024 [13] | Taiwan | Women aged 40–69 years | DBT-DM | Biennial | ICER | No |
| Couto et al. 2024 [23] | Brazil | Women aged 40–69 years with BI-RADS B or C | DBT with s2D | Biennial | ICER | Siemens Healthineers |
| Cressman et al. 2021 [47] | Canada | Women aged 40–74 years | DBT-DM | Biennial | ICER | No |
| Fridhammar et al. 2025 [49] | Sweden | Women aged 40–74 years | DBT | 1.5–2 years | Relative reduction in breast cancer mortality for DBT to be cost effective | No |
| Kalra et al. 2016 [25] | USA | Women aged 40–79 years | DBT-DM | Annual | ICER | No |
| Lee et al. 2015 [24] | USA | Women aged 50–74 years with dense breasts | DBT-DM | Biennial | ICER | No |
| Lowry et al. 2020 [44] | USA | Women aged 40–79 years | DBT-DM | 1–2 years | ICER | No |
| Moger et al. 2022 [48] | Norway | Women aged 50–69 years | DBT with s2D | Biennial | ICER | No |
| Sankatsing et al. 2020 [45] | Netherlands | Women aged 50–74 years | DBT | Biennial | ICER | No |
| Wang et al. 2020 [46] | Netherlands | Women aged 50–75 years | DBT | Biennial | Sensitivity at which DBT would be cost effective | No |
Table 4.
Model characteristics
| Publication | Evaluation type | Model type | Perspective | Time horizon (years) | Discount rate (%) | Cost estimation | Currency, cost year |
|---|---|---|---|---|---|---|---|
| Chung et al. 2024 [13] | CUA | State transition cohort model | Societal | 30 | 2 | Direct and indirect | $, 2021 |
| Couto et al. 2024 [23] | CUA | Decision tree with state transition model | Payer | 30 | 5 | Direct | €, 2023 |
| Cressman et al. 2021 [47] | CUA | State transition cohort model | Payer | 40 | 3 | Direct | C$, 2019 |
| Fridhammar et al. 2025 [49] | CUA | Unclear | Payer | Lifetime | 3 | Direct | €, 2022 |
| Kalra et al. 2016 [25] | CUA | State transition cohort model | Payer | Lifetime | 3 | Direct | $, 2015 |
| Lee et al. 2015 [24] | CUA | Discrete event simulation | Payer | Lifetime | 3 | Direct | $, 2013 |
| Lowry et al. 2020 [44] | CUA | Discrete event simulation and analytical approach | Payer | Lifetime | 3 | Direct | $, 2018 |
| Moger et al. 2022 [48] | CEA | Decision tree model | NR | 10 | 4 | Direct | €, 2018 |
| Sankatsing et al. 2020 [45] | CEA | Microsimulation | NR | Lifetime | 3.5 | Direct | €, 2020 |
| Wang et al. 2020 [46] | CEA | Microsimulation | NR | Lifetime | 3 | Direct | €, NR |
Table 5.
Test performance of mammographic screenings reported
| Publication | Sensitivity (%) | Specificity (%) | Recall rate (%) | Source(s) | |||
|---|---|---|---|---|---|---|---|
| Intervention | Comparator | Intervention | Comparator | Intervention | Comparator | ||
| Chung et al. 2024 [13] | – | – | – | – | 9.0 | 11.8 | Retrospective cohort study [52] |
| Couto et al. 2024 [23] | – | – | – | – | 3.5 | 4.2 | Meta-analysis [23] |
| Cressman et al. 2021 [47] | – | – | – | – | Absolute reduction of 2.2 | Meta-analysis [15] | |
| Fridhammar et al. 2025 [49] | – | – | – | – | 3.6 | 2.5 | Prospective cohort study [19] |
| Kalra et al. 2016 [25] | – | – | – | – | 9.1 | 10.7 | Retrospective cohort study [53] |
| Lee et al. 2015 [24] | 80 | 77 | 92 | 88 | – | – | Prospective cohort study [54] |
| Lowry et al. 2020 [44] | 84.3–96.8 | 88.2–95.8 | 76.6–91.1 | 65.5–84.3 | – | – | Prospective cohort study [55, 56] |
| Moger et al. 2022 [48] | – | – | – | – | 4.4 | 4.3 | RCT [50] |
| Sankatsing et al. 2020 [45] | 18 increase | – | – | – | – | Expert estimation and prospective cohort studies [57, 58] | |
| Wang et al. 2020 [46] | 65–100 | 65–87 | 96.5 | 96.5 | – | – | DBT performance: assumption; DM sensitivity: retrospective cohort study [59]; DM specificity: RCT [60] |
Table 6.
Base-case cost-effectiveness results for DBT-DM
| Publication | Intervention | Comparator | Incremental cost | Incremental QALYs | ICER (QALYs) | ICER threshold (QALYs) | ΔNMB | ICER (2023) | Author’s conclusions on cost-effectiveness | ||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Mean QALYs | Mean total cost | Mean QALYs | Mean total cost | ||||||||
| Chung et al. 2024 [13] | 22.994 | $7,861.1 | 22.954 | $7,621.7 | $239.4 | 0.04 | $5,972 | $33,004 | $1,084 | I$6,624 | Cost effective |
| Cressman et al. 2021 [47] | NR | NR | NR | NR | C$470 | 0.027 | C$17,149 | C$100,000 | C$2,230 | I$17,930 | Cost effective |
| Kalra et al. 2016 [25] | 15.5 | $15,312 | 15.46 | $14,500 | $812 | 0.04 | $20,300 | $100,000 | $3,188 | I$25,532 | Cost effective |
| Lee et al. 2015 [24] | 16.814 | $4,440 | 16.807 | $4,091 | $349 | 0.007 | $53,893 | $100,000 | $351 | I$70,698 | Cost effective |
| Lowry et al. 2020† [44] | 14,914–15,757 | $4.6–5.0 | 14,912–15,756 | $4.2–4.6 | $0.40–0.45 | 1.7–2.2 | $195,026–270,135 | $50,000–150,000 | – | I$233,266–323,103 | Not cost effective |
Table 7.
Base-case cost-effectiveness results for DBT
| Publication | Intervention | Comparator | Incremental cost | Incremental QALYs | ICER (QALYs) | ICER threshold (QALYs) | ΔNMB | Author’s conclusions on cost-effectiveness | ||
| Mean QALYs | Mean total cost | Mean QALYs | Mean total cost | |||||||
| Couto et al. 2024 [23] | 18.919 | €2,094.5 | 13.720 | €3,048.6 | –€954.02 | 5.199 | Dominates | €7,200 | €38,386 | Cost effective (dominant) |
| Fridhammar et al. 2025† [49] | –613.9 to –581.1 | €12.81–13.13 | –630.0 | €12.32 | €0.49–0.80 | 16.1–48.9 | – | €10,000–50,000 | – | Cost effective when the relative breast cancer mortality reduction is 3.6%–10.1% |
| Publication | Intervention | Comparator | Incremental cost | Incremental LYs | ICER (LYs) | ICER threshold (LYs) | ΔNMB | Author’s conclusions on cost-effectiveness | ||
| Mean LYs | Mean total cost | Mean LYs | Mean total cost | |||||||
| Moger et al. 2022‡ [48] | NR | NR | NR | NR | –€50,000 | 34.8 | Dominates | € 22,000 | €815,600 | Cost effective (dominant) |
| Sankatsing et al. 2020§ [45] | 73 | €443,385 | 67 | €305,829 | €137,555 | 5.09 | €27,023 (I$43,311) | €20,000–35,000 | –€35,755–40,650 | Inconclusive |
| Wang et al. 2020 [46] | NR | NR | NR | NR | NR | –76–120 (per 10,000) | – | €20,000 | – | Cost-effective when sensitivity is at least 95% |
Table 8.
Sensitivity analyses and primary drivers of cost-effectiveness
| Publication | Analysis type | Probability that DBT is cost-effective (%) | Key parameters influencing ICER | Structural uncertainty | |
|---|---|---|---|---|---|
| Parameter | Range varied or alternative assumption | ||||
| Chung et al. 2024 [13] | Deterministic and probabilistic | 98.5 | Recall rate of DBT-DM | [8.1%, 9.9%] (prior literature) | Shorter time horizon (10 years) |
| Couto et al. 2024 [23] | Deterministic and probabilistic | 100 | Cancer detection rate of DM | Unclear (±25% variation or 95% CI) | NR |
| Cressman et al. 2021 [47] | Deterministic and probabilistic | 95 | Recall rate reduction | [1%, 7.7%] (unclear assumption) | NR |
| Kalra et al. 2016 [25] | Deterministic and probabilistic | 63.2 | Unclear | – | NR |
| Lee et al. 2015 [24] | Deterministic | – | Adjunct DBT cost | [$0, $139] (no additional cost and cost doubled) | NR |
| Lowry et al. 2020 [44] | Deterministic | – | Adjunct DBT cost | $26 and $36 from base price of $56 | NR |
| Moger et al. 2022 [48] | Deterministic and probabilistic | 80 | Unclear | – | Extended time horizon (20 years) |
| Sankatsing et al. 2020 [45] | Deterministic and probabilistic | 36–66% | DBT cost | [€72, €125] (expert estimation) | NR |
Table 9.
Reporting quality assessment
| Study/Item No. | 1 | 2 | 3 | 4 | 5 | 6 | 7 | 8 | 9 | 10 | 11 | 12 | 13 | 14 | 15 | 16 | 17 | 18 | 19 | 20 | 21 | 22 | 23 | 24 | 25 | 26 | 27 | 28 | 29 | 30 | 31 | 32 | 33 | 34 | 35 | % yes |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Chung et al. 2024 [13] | Y | Y | Y | Y | Y | Y | Y | Y | UC | NA | Y | UC | N | Y | Y | N | Y | Y | Y | Y | Y | Y | Y | UC | NA | NA | Y | Y | UC | Y | Y | Y | Y | UC | Y | 78.1 |
| Couto etal. 2024 [23] | Y | Y | Y | Y | Y | Y | Y | Y | NA | Y | Y | Y | N | NA | NA | Y | Y | Y | UC | Y | Y | Y | Y | Y | NA | Y | Y | Y | UC | Y | Y | Y | Y | Y | Y | 90.3 |
| Cressman etal. 2021 [47] | Y | Y | Y | Y | Y | Y | Y | Y | Y | NA | Y | N | N | NA | NA | N | Y | Y | Y | Y | Y | Y | Y | Y | NA | Y | Y | Y | Y | Y | Y | N | Y | Y | Y | 87.1 |
| Fridhammar et al. 2025[49] | Y | Y | Y | Y | Y | Y | Y | Y | Y | NA | Y | UC | Y | NA | NA | N | Y | Y | Y | UC | Y | Y | Y | Y | NA | NA | Y | Y | UC | Y | Y | Y | N | Y | Y | 83.3 |
| Kalra et al. 2016 [25] | Y | Y | Y | Y | Y | Y | Y | Y | UC | NA | Y | N | N | NA | NA | N | Y | Y | Y | Y | Y | Y | Y | Y | NA | NA | Y | Y | Y | Y | Y | Y | Y | Y | Y | 86.7 |
| Lee et al. 2015 [24] | Y | UC | Y | Y | Y | Y | Y | Y | UC | NA | Y | Y | N | NA | NA | N | Y | Y | Y | Y | Y | Y | Y | Y | NA | NA | Y | Y | Y | Y | Y | Y | Y | Y | Y | 86.7 |
| Lowry et al. 2020 [44] | Y | Y | Y | Y | Y | Y | Y | Y | Y | NA | Y | N | N | NA | NA | N | Y | Y | UC | Y | Y | Y | Y | Y | NA | NA | Y | Y | UC | Y | Y | Y | Y | Y | Y | 83.3 |
| Moger et al. 2022 [48] | Y | Y | N | Y | Y | Y | Y | Y | Y | NA | Y | Y | Y | NA | NA | N | Y | Y | Y | Y | Y | Y | Y | Y | NA | NA | Y | Y | N | Y | Y | Y | Y | UC | Y | 86.7 |
| Sankatsing et al. 2020 [45] | Y | Y | N | Y | Y | Y | UC | Y | NA | NA | Y | Y | Y | NA | NA | N | Y | Y | Y | Y | Y | Y | Y | UC | NA | NA | Y | Y | N | Y | Y | Y | Y | Y | Y | 82.8 |
| Wang etal. 2020 [46] | Y | Y | N | Y | Y | Y | UC | Y | NA | N | Y | Y | Y | NA | NA | N | Y | Y | N | Y | Y | Y | Y | Y | NA | NA | Y | Y | Y | Y | Y | N | Y | Y | Y | 80.0 |
| 1. digital breast tomosynthesis/ | 2537 |
| 2. (“3-D mammogra$” or “3D mammogra$” or “three dimensional mammogra$” or “3-dimensional mammogra$”).ti,ab. | 146 |
| 3. (tomosynthesis adj6 (breast$ or mammar$)).ti,ab. | 2413 |
| 4. (“3Dimensions” or “Selenia Dimensions” or “Senographe Pristina” or “VolumeRAD” or “Wide-Angle Tomosynthesis” or “Helianthus” or “ASPIRE Cristalle” or “Amulet Innovality” or “Planmed Clarity” or “Giotto Class”).ti,ab. | 2853 |
| 5. Health Economics/ | 37479 |
| 6. exp Economic Evaluation/ | 395752 |
| 7. exp Health Care Cost/ | 373813 |
| 8. pharmacoeconomics | 22712 |
| 9. 5 or 6 or 7 or 8 | 702379 |
| 10. (econom$ or cost or costs or costly or costing or price or prices or pricing or pharmacoeconomic$).ti,ab. | 1628716 |
| 11. (expenditure$ not energy).ti,ab. | 56798 |
| 12 (value adj2 money).ti,ab. | 3324 |
| 13 budget$.ti,ab. | 53134 |
| 14 10 or 11 or 12 or 13 | 1678856 |
| 15 9 or 14 | 1948472 |
| 16 letter.pt. | ` 1367862 |
| 17 editorial.pt. | 840046 |
| 18 note.pt. | 1011807 |
| 19 16 or 17 or 18 | 3219715 |
| 20 15 not 19 | 1823610 |
| 21 (metabolic adj cost).ti,ab. | 2102 |
| 22 ((energy or oxygen) adj cost).ti,ab. | 5543 |
| 23 ((energy or oxygen) adj expenditure).ti,ab. | 42102 |
| 24 21 or 22 or 23 | 48417 |
| 25 20 not 24 | 1813783 |
| 26 animal/ | 1714835 |
| 27 exp animal experiment/ | 3376239 |
| 28 nonhuman/ | 8196933 |
| 29 (rat or rats or mouse or mice or hamster or hamsters or cat or cats or bovine or sheep).ti,ab,sh.or animal or animals or dog or dogs | 6980972 |
| 30 26 or 27 or 28 or 29 | 11257887 |
| 31 exp human/ | 28645138 |
| 32 human experiment/ | 719122 |
| 33 31 or 32 | 28648462 |
| 34 30 not (30 and 33) | 7810731 |
| 35 25 not 34 | 1629519 |
| 36 1 or 2 or 3 or 4 | 6081 |
| 37 35 and 36 | 363 |
| 1 (“3-D mammogra$” or “3D mammogra$” or “three dimensional mammogra$” or “3-dimensional mammogra$”).ti,ab. | 74 |
| 2 (tomosynthesis adj6 (breast$ or mammar$)).ti,ab. | 1861 |
| 3 (“3Dimensions” or “Selenia Dimensions” or “Senographe Pristina” or “VolumeRAD” or “Wide-Angle Tomosynthesis” or “Helianthus” or “ASPIRE Cristalle” or “Amulet Innovality” or “Planmed Clarity” or “Giotto Class”).ti,ab. | 3047 |
| 4 1 or 2 or 3 | 4891 |
| 5 Economics/ | 27549 |
| 6 exp “costs and cost analysis“/ | 279639 |
| 7 Economics, Dental/ | 1922 |
| 8 exp economics, hospital/ | 26225 |
| 9 Economics, Medical/ | 9306 |
| 10 Economics, Nursing/ | 4013 |
| 11 Economics, Pharmaceutical/ | 3164 |
| 12 (economic$ or cost or costs or costly or costing or price or prices or pricing or pharmacoeconomic$).ti,ab. | 1220002 |
| 13 (expenditure$ not energy).ti,ab. | 41338 |
| 14 value for money.ti,ab. | 2399 |
| 15 budget$.ti,ab. | 39892 |
| 16 or/5–15 | 1392581 |
| 17 ((energy or oxygen) adj cost).ti,ab. | 5151 |
| 18 (metabolic adj cost).ti,ab. | 1893 |
| 19 ((energy or oxygen) adj expenditure).ti,ab. | 31483 |
| 20 or/17–19 | 37408 |
| 21 16 not 20 | 1383880 |
| 22 exp animals/not humans/ | 5349190 |
| 23 21 not 22 | 1296959 |
| 24 4 and 23 | 283 |
| 1 (“3-D mammogra$” or “3D mammogra$” or “three dimensional mammogra$” or “3-dimensional mammogra$”).ti,ab. | 3 |
| 2 (tomosynthesis adj6 (breast$ or mammar$)).ti,ab. | 53 |
| 3 (“3Dimensions” or “Selenia Dimensions” or “Senographe Pristina” or “VolumeRAD” or “Wide-Angle Tomosynthesis” or “Helianthus” or “ASPIRE Cristalle” or “Amulet Innovality” or “Planmed Clarity” or “Giotto Class”).ti,ab. | 1 |
| 4 1 or 2 or 3 | 54 |
| #1 ((3D NEXT mammogra*) or (3 NEXT D NEXT mammogra*) or (three NEXT dimensional NEXT mammogra*) or (3 NEXT D NEXT mammogra*)):ti,ab | 3 |
| #2 ((tomosynthesis NEAR/6 breast*) or (tomosynthesis NEAR/6 mammar*)):ti,ab | 76 |
| #3 (3Dimensions or “Selenia Dimensions” or “Senographe Pristina” or “VolumeRAD” or “Wide-Angle Tomosynthesis” or Helianthus or “ASPIRE Cristalle” or “Amulet Innovality” or “Planmed Clarity” or “Giotto Class”):ti,ab | 22 |
| #4 #1 or #2 or #3 | 101 |
| (“3-D mammogram” or “3-D mammograms” or “3-D mammography” or “3-D mammographies” or “3D mammogram” or “3D mammograms” or “3D mammography” or “3D mammographies” or “three dimensional mammogram” or “three dimensional mammograms” or “three dimensional mammography” or “three dimensional mammographies” or “three-dimensional mammogram” or “three-dimensional mammograms” or “three-dimensional mammography” or “three-dimensional mammographies”) OR (tomosynthesis) | 1 |
| “3-D mammogram” OR “3-D mammograms” OR “3-D mammography” OR “3-D mammographies” OR “3D mammogram” OR “3D mammograms” OR “3D mammography” OR “3D mammographies” OR “three dimensional mammogram” OR “three dimensional mammograms” OR “three dimensional mammography” OR “three dimensional mammographies” OR “three-dimensional mammogram” OR “three-dimensional mammograms” OR “three-dimensional mammography” OR “three-dimensional mammographies” OR tomosynthesis | 6 |
| “3-D mammogram” | “3-D mammograms” | “3-D mammography” | “3-D mammographies” | “3D mammogram” | “3D mammograms” | “3D mammography” | “3D mammographies” | “three dimensional mammogram” | “three dimensional mammograms” | “three dimensional mammography” | “three dimensional mammographies” | “three-dimensional mammogram” | “three-dimensional mammograms” | “three-dimensional mammography” | “three-dimensional mammographies” | tomosynthesis | 21 |